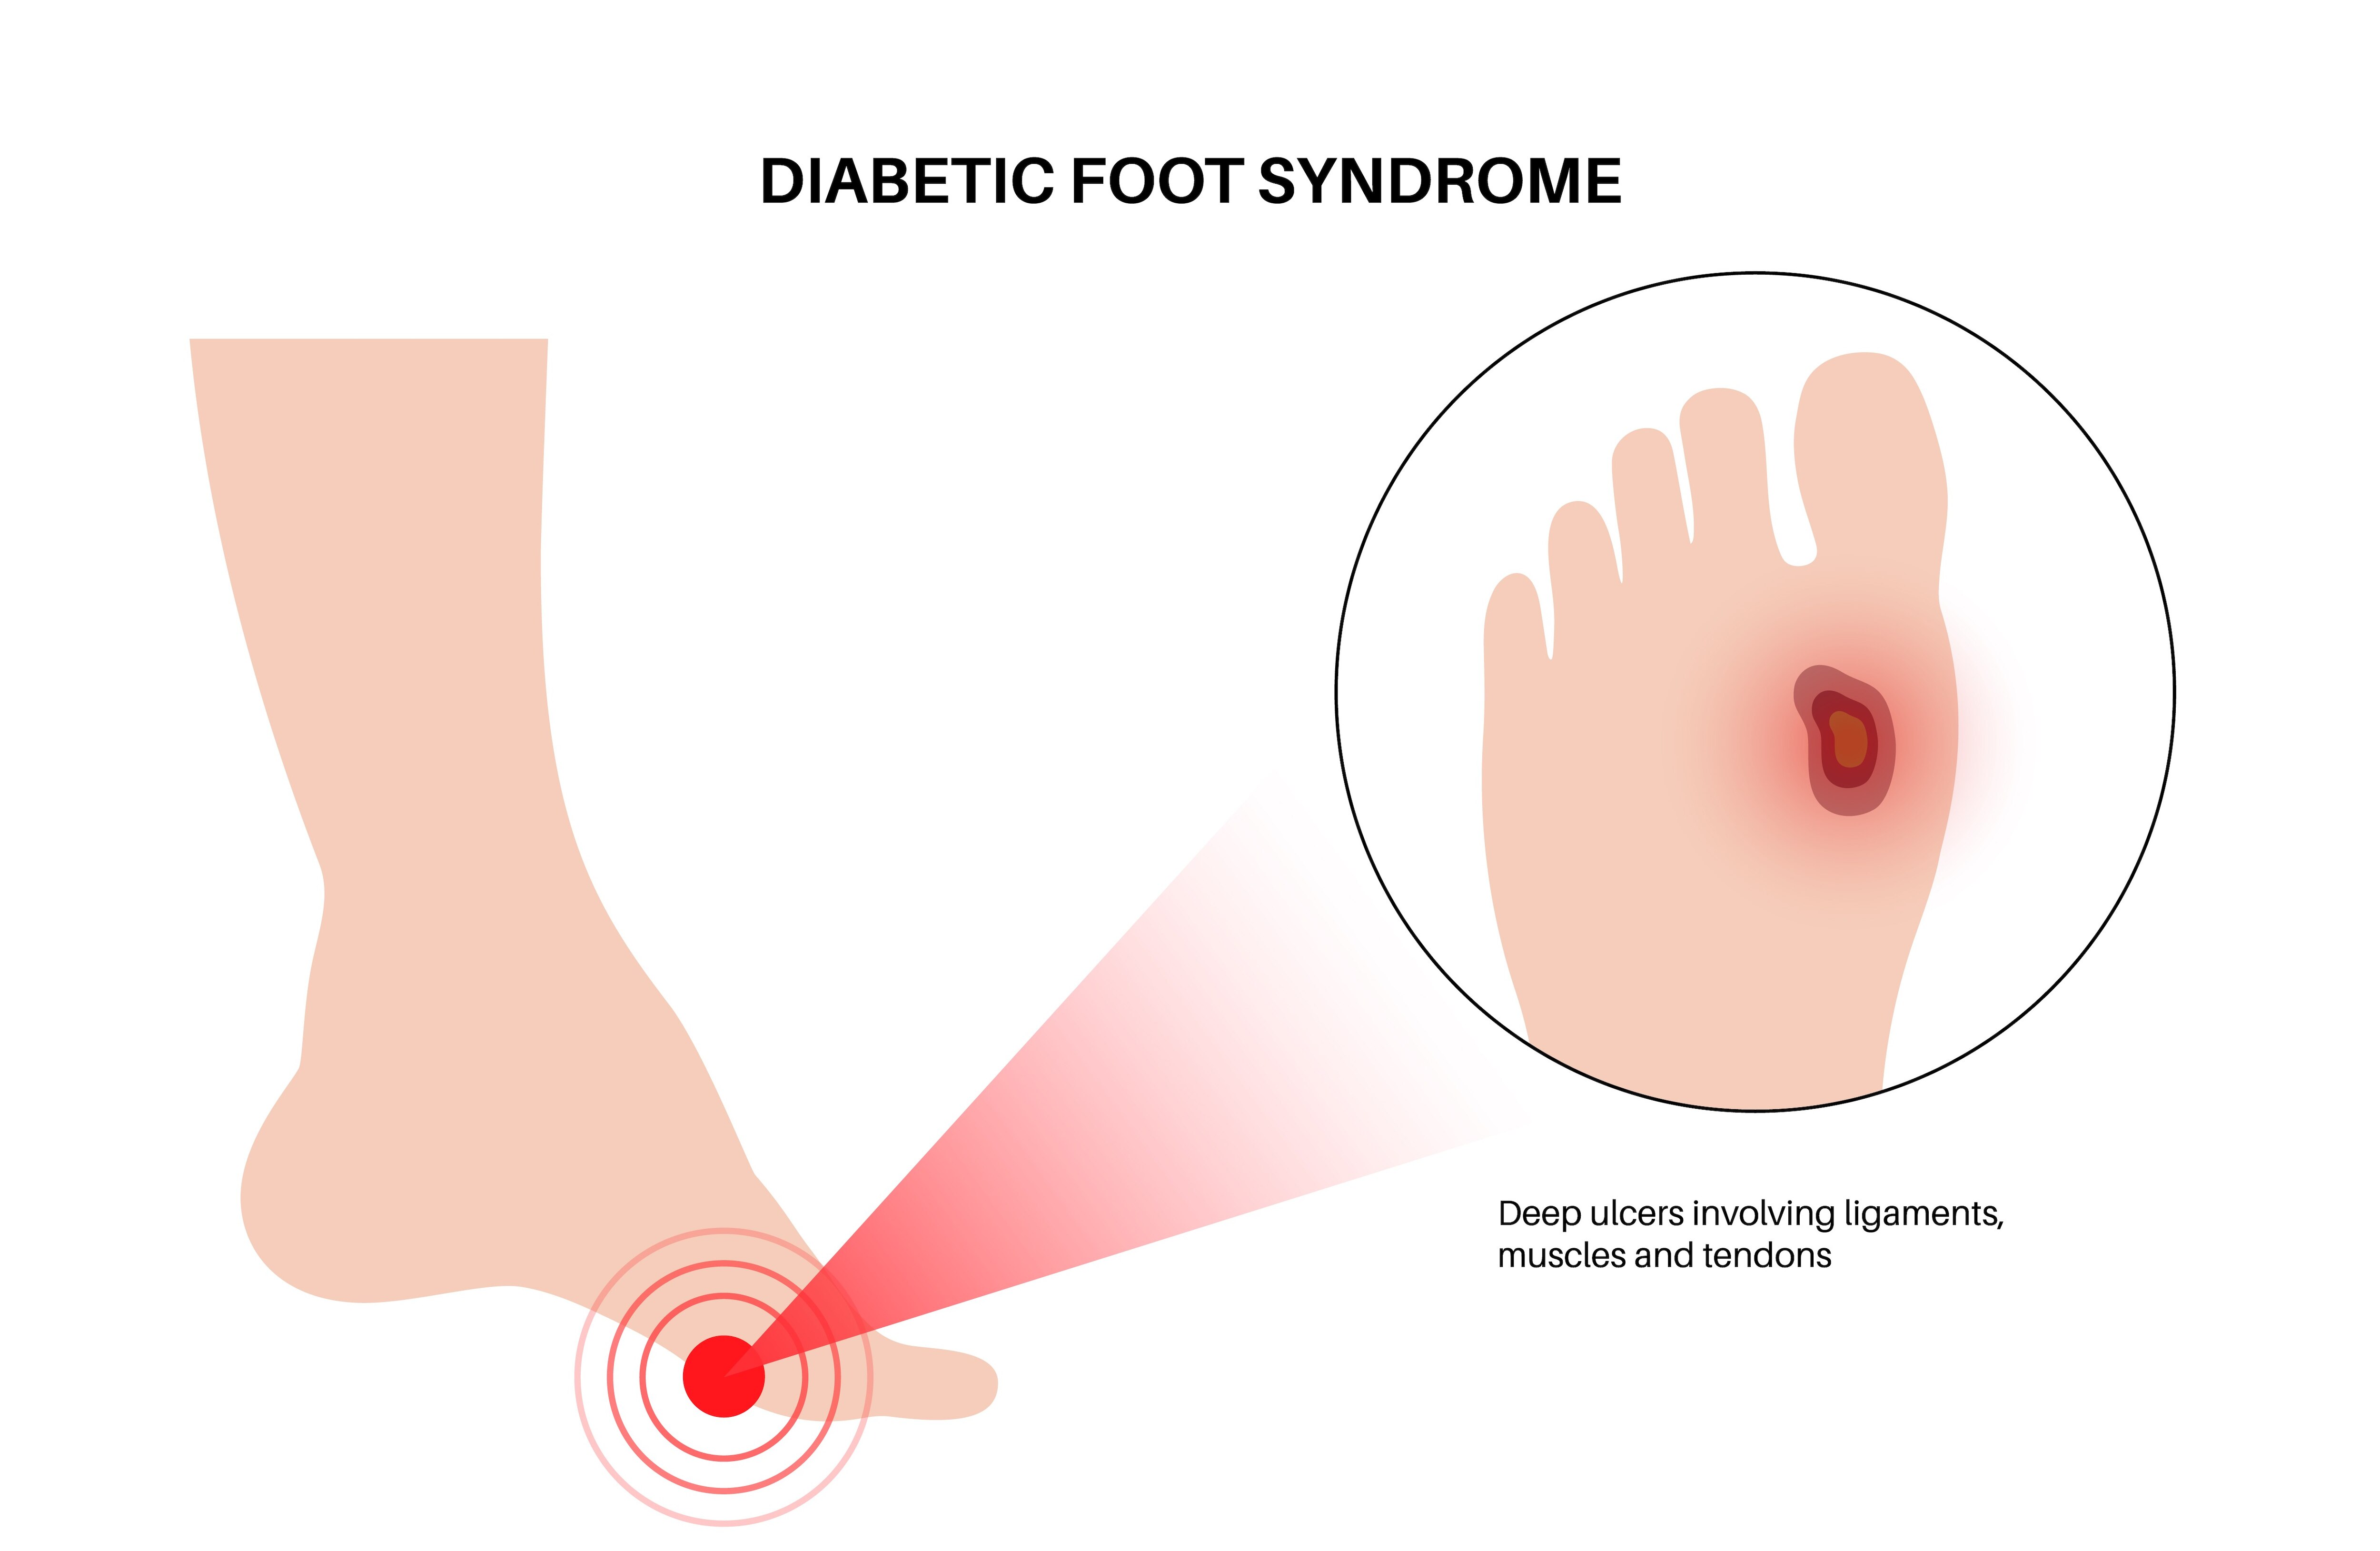
A diabetic foot operation is not one standard procedure: the plan depends on infection, blood flow, tissue damage, pressure and the possibility of healing afterward. You will learn what the surgeon examines, which procedures may be included, when non-surgical treatment is safer, and what care continues after surgery.
Key takeaways
- Debridement removes dead tissue; amputation is reserved for tissue that cannot be saved.
- Ask whether blood flow, infection depth and bone involvement were assessed before surgery.
- Pressure relief is essential when a wound will not heal under repeated loading.
- Choose a service offering wound care, vascular assessment and follow-up after the operation.
What procedures are included in diabetic foot surgery?
Diabetic foot surgery in Mumbai can range from limited wound treatment to amputation. Procedures include sharp debridement of dead tissue, abscess drainage, removal of infected bone, toe or ray amputation, transmetatarsal amputation, or a higher-level amputation when the tissue cannot be saved.
The visible ulcer size does not determine the operation. The surgeon assesses viable tissue, how far infection has spread, arterial blood supply and whether the result can support durable weight-bearing. A small opening can hide deep infection; a larger ulcer may heal after dead tissue is removed and pressure is controlled.
Seek same-day surgical assessment if you have:
- Redness or swelling spreading beyond the wound
- Pus or a foul odour
- Black or grey tissue
- Fever or chills
- New confusion
- Severe pain despite numbness
- Visible tendon or bone
Neuropathy damages the protective sensation that normally makes you withdraw from pressure, heat or injury. Infection can therefore worsen while the foot feels normal, so waiting for pain is unsafe. Severe pain despite numbness is especially concerning because it can signal deep tissue pressure or infection rather than a routine ulcer.
Do not delay assessment while trying home dressings if any warning sign appears.
How does a surgeon decide whether you need an operation?
Surgery is considered when dead tissue, a drainable abscess, deep infection, exposed bone, or threatened blood supply cannot be managed safely with dressings, antibiotics, off-loading footwear or casting.
If infection is superficial and circulation is adequate, wound care and pressure relief may be safer; if blood flow is poor, vascular treatment may come before foot surgery.
Before recommending a diabetic foot operation in Mumbai, the surgeon checks:
- Wound size, depth, undermining, and exposed tendon or bone
- Foot pulses, skin temperature, colour, and sensation
- Blood glucose and HbA1c
- Kidney function, blood count, nutrition, smoking, and medication or anticoagulant use
- Ability to remain non-weight-bearing after surgery; inability to protect the foot can make an otherwise suitable operation unsafe
- Plain X-ray, arterial Doppler, toe pressure or toe-brachial index, tissue culture, and MRI when osteomyelitis remains uncertain
An ulcer that probes to bone raises suspicion of osteomyelitis but does not prove bone infection; examination, imaging and appropriately collected deep samples determine the diagnosis. A plain X-ray is usually an early test, while MRI helps when uncertainty remains.
Do not rely on a reassuring ankle-brachial index alone: diabetes can calcify ankle arteries and make the result falsely reassuring. The final choice balances infection, viable tissue, circulation, healing capacity and whether you can achieve durable, protected weight-bearing without unnecessary tissue removal.
How do infection and poor circulation change the operation?
The operation follows the main threat: infection requires source control, while poor circulation requires restoration of blood flow before tissue can heal.
| Threat | How the operation changes | What may happen next |
|---|---|---|
| Deep infection or tissue death | Urgent assessment, early removal of non-viable tissue, abscess drainage and deep tissue or bone sampling | Staged debridement, infected-bone removal or amputation, with antibiotics |
| Poor blood supply | Vascular imaging and assessment for revascularisation before or alongside wound surgery | Closure or reconstruction waits until perfusion can support healing |
Deep infection, wet gangrene, necrotising infection, compartment syndrome or an abscess that cannot be drained adequately through a minor procedure needs urgent surgical assessment. A diabetic foot operation in Mumbai may involve sharp debridement, drainage, removal of infected bone or amputation, often within 24–48 hours when clinically indicated.
A deep tissue or bone sample is more useful than a surface swab for guiding treatment.
Antibiotics support source control; they do not replace drainage or debridement. Do not take antibiotics simply to heal an uninfected ulcer.
Poor circulation can make even a technically successful operation fail. Seek urgent vascular input when ankle pressure is below 50 mmHg, ABI below 0.5, toe pressure below 30 mmHg or transcutaneous oxygen below 25 mmHg. Revascularisation may precede debridement or amputation, or accompany it. Leave closure, grafting or reconstruction until blood flow is adequate.
What happens when pressure causes a non-healing wound?
A neuropathic plantar ulcer needs pressure removed before tissue is repaired. For a forefoot or midfoot ulcer without contraindications, a non-removable knee-high off-loading device is usually first-line. If effective off-loading fails or cannot be used, surgery may correct a deformity, release a tendon or remove a pressure point.
Skin grafting or reconstruction comes later, after the wound bed is viable, infection is controlled and blood supply is adequate. A contaminated wound may stay open; staged debridement, delayed closure or negative-pressure therapy allows drainage and reinspection instead of trapping infection beneath closed skin.
After foot wound surgery in Mumbai, follow the pressure-relief plan precisely:
- Use protected weight-bearing as instructed.
- Wear the prescribed cast or footwear rather than ordinary shoes.
- Attend dressing checks and report increasing drainage, odour or wound separation.
- Keep glucose and kidney-function management under review.
- Avoid smoking where applicable.
- Inspect both feet every day, including the sole and between the toes.
A new amputation stump can fail if pressure creates another ulcer or infection enters the incision. Swelling, redness, discharge, fever or a new dark area needs prompt assessment, because neuropathy can hide the pain that would otherwise warn you.
What should you look for in a diabetic foot surgical service?
Choose a diabetic foot surgeon in Mumbai by checking the service’s coordination, not by assuming one specialist performs every part of care. Infection, blood-flow problems, glucose control and mobility often require different clinicians.
Ask these questions before agreeing to treatment:
- Can you arrange sharp wound debridement, deep tissue or bone sampling, and abscess treatment rather than relying on a surface swab?
- Who will perform arterial testing, and who will arrange vascular imaging or revascularisation if ankle pressure, toe pressure or Doppler findings show poor inflow?
- Who will provide pressure relief through a cast, prescribed footwear or another off-loading device, and decide whether deformity correction is needed?
- Who will optimise glucose, kidney function and medicines before surgery?
- Who will manage rehabilitation, protected weight-bearing and postoperative mobility?
- How will you monitor the opposite foot, and what signs trigger urgent escalation?
The consultation should leave you with named responsibilities, a dressing and weight-bearing plan, review dates, and clear instructions for fever, spreading redness, worsening drainage or a darkening wound.
A consultation with Dr Vipul Nandu’s general and laparoscopic surgical practice in Mumbai can help establish whether your case needs an operation, coordinated vascular input, staged wound care or continued non-operative treatment. The useful outcome is a defined pathway, not an automatic procedure.
Related service
Diabetic Foot Surgery Diabetic foot surgery is a specialized surgical procedure aimed at treating complications of diabetes that affect the feet. View service → |
Frequently asked questions
What procedures are included in diabetic foot surgery?
Procedures include sharp debridement, abscess drainage, infected-bone removal, toe or ray amputation, transmetatarsal amputation and higher-level amputation when tissue cannot be saved.
How does a surgeon decide whether you need an operation?
The surgeon assesses the wound, dead tissue, infection, bone involvement, blood flow, pressure on the area and whether non-surgical treatment is healing it.
How do infection and poor circulation change the operation?
Deep infection can require drainage, debridement or removal of infected bone. Poor circulation can prevent healing, so the surgeon must assess blood flow and address it before or alongside surgery.
What happens when pressure causes a non-healing wound?
The service must remove dead or infected tissue when necessary and reduce pressure with appropriate footwear, offloading, wound care and follow-up.
What should you look for in a diabetic foot surgical service?
Look for wound assessment, infection and blood-flow evaluation, appropriate surgical options, pressure relief planning and structured post-operative follow-up.
Keywords